




Tubal Assessment: Hysterosalpingogram
Tubal assessment is the set of tests that establish whether your fallopian tubes are open, and whether the uterine cavity looks normal. It is one of the first investigations arranged when a couple has been trying without success, because a blocked tube changes the treatment plan more decisively than almost any other finding.
This page explains what tubal assessment involves at Jananam Fertility Centre, which of the three available tests suits which situation, when in your cycle it is done, and what the result actually changes. If you want the procedure itself explained in detail, that is on our separate page about the HSG test.
On this page
- What tubal assessment means
- Why the tubes matter this much
- The three tests, and which one when
- When tubal assessment is recommended
- When in your cycle it is done
- When it should be postponed
- What the result changes
- The flushing effect
- Questions patients ask
What tubal assessment means
Tubal assessment is not a single test. It is a question — can an egg and sperm meet, and can an embryo reach the uterus? — answered by whichever test fits the individual.
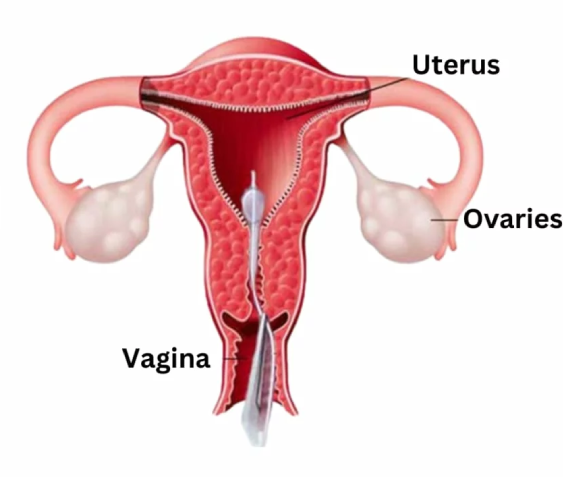
All three available tests work the same way in principle: a fluid is passed through the cervix into the uterus, and the clinician watches whether it travels along each tube and spills out of the far end. Free spill means that tube is open, or patent. The tests differ in what is used to watch, not in what is being asked.
The same tests also show the shape of the uterine cavity, which is why tubal assessment often answers a second question nobody had asked yet.
Why the tubes matter this much
In natural conception and in IUI, fertilisation happens inside the fallopian tube. Sperm travel up; the egg is collected by the tube after ovulation; they meet there; the resulting embryo is carried down to the uterus over several days.
If both tubes are blocked, none of that can happen — and no amount of ovulation tracking or IUI will change it. IVF bypasses the tubes entirely, which is why it is the appropriate route when both are blocked.
If one tube is open, natural conception remains possible. This is the distinction that makes the test worth doing rather than assuming: “blocked tubes” and “one blocked tube” lead to different conversations. Fallopian tube problems covers the underlying causes in more depth.
The three tests, and which one when
We do not use one test for everybody, and which one is right depends on what else is going on.
| Test | How the tubes are seen | Usually chosen when |
|---|---|---|
| HSG (hysterosalpingogram) | X-ray with iodinated contrast dye | First-line where tubal patency is the main question. Gives a permanent image of the cavity and tubes. |
| HyCoSy / HyFoSy | Ultrasound with a foam or saline contrast — no radiation | Where avoiding X-ray matters, where an ultrasound is being done anyway, or where iodine is not suitable. |
| Laparoscopy with dye | Direct view inside the pelvis under anaesthesia | Where endometriosis or adhesions are suspected, or where a less invasive test was inconclusive. It is the only one that also treats what it finds. |
The first two are outpatient procedures done without general anaesthesia. Laparoscopy is surgery, so it is not a starting point — but it is the most informative of the three, because the clinician is looking directly rather than inferring from a shadow or an echo.
Our page on HyCoSy and HyFoSy sets out the ultrasound-based option in detail. Where the question is about the cavity rather than the tubes, hysteroscopy looks inside the uterus directly.
When tubal assessment is recommended
Typically in one of these situations:
- Trying to conceive for a year without success, or six months if you are over 35
- Before starting IUI — there is no point stimulating a cycle if the tubes cannot carry an embryo
- A history of pelvic infection, appendicitis, pelvic surgery or a previous ectopic pregnancy, all of which can affect the tubes
- Known or suspected endometriosis
- Unexplained infertility — where tubal assessment is part of what makes that label honest rather than premature
The NICE fertility guideline (CG156) sets out where tubal testing sits in the wider investigation sequence.
When in your cycle it is done
Tubal assessment is scheduled in the first half of the cycle — broadly days 6 to 12, once bleeding has stopped and before ovulation.
There are two reasons, and both matter. Bleeding would obscure the images and can push debris along the tubes. And testing before ovulation means there is no possibility of an early pregnancy in the uterus at the time.
So the appointment is usually booked by counting from the first day of your period. If your cycle arrives earlier or later than expected, tell us and we will move it — this is a common reason for rescheduling and not an inconvenience.
When it should be postponed
Tubal assessment is not appropriate if any of the following applies:
- Known or possible pregnancy
- An active pelvic infection, including untreated pelvic inflammatory disease — passing fluid through an infected uterus can spread infection upwards, so infection is treated first and the test follows
- Heavy uterine bleeding at the time of the appointment
- A known allergy to iodinated contrast — which does not rule out tubal assessment, only the X-ray version of it. HyFoSy is the alternative
One correction worth stating plainly, because it appears widely and appeared on this page previously: endometriosis is not a reason to avoid tubal assessment. It is one of the reasons to do it. What endometriosis may change is which test is chosen — it is a common reason to prefer laparoscopy, which can see and treat the disease in the same procedure.
What the result changes
This is the question we would want you to ask about any test, and it has a clear answer here.
Both tubes open. Tubal factor is excluded, and the investigation moves on to ovulation, sperm and the uterine cavity. IUI remains on the table.
One tube open. Natural conception and IUI remain possible. Which side is open can matter, and is taken into account in timing.
Both tubes blocked. IVF is the route that works, because it bypasses the tubes. This is a redirection rather than a setback, and it is better known early than after months of treatment aimed at the wrong thing.
A tube blocked and swollen with fluid. This is hydrosalpinx, and it is treated differently from a simple blockage — the fluid itself can interfere with implantation, so it is usually addressed before an embryo transfer rather than worked around.
A common result deserves mention: a tube can appear blocked on one test and open on another. Spasm at the narrow end of the tube can mimic a blockage. A single unexpected finding is often a reason to repeat or cross-check rather than to conclude.
The flushing effect
There is a genuine, published observation that some couples conceive in the months after tubal assessment, apparently because passing contrast through the tubes clears minor debris. Randomised trial evidence supports a real effect with oil-based contrast in particular.
We mention it because patients hear about it and ask. Two honest qualifications: it is not the reason the test is done, and it is not something we would offer as a treatment in its own right. The test is a diagnostic, and any benefit beyond the information is a welcome side effect rather than the purpose.
Questions patients ask
What is tubal assessment?
It is the investigation that establishes whether the fallopian tubes are open and whether the uterine cavity is normal, by passing a fluid through the uterus and watching whether it travels along each tube and spills out. It can be done by X-ray (HSG), by ultrasound (HyCoSy or HyFoSy), or at laparoscopy.
Is tubal assessment painful?
Most women describe cramping similar to period pain, lasting a few minutes, rather than sharp pain. The outpatient tests are done without general anaesthesia and you can usually resume normal activity the same day. Taking simple pain relief an hour beforehand helps, and is worth asking us about.
Which is better, HSG or HyCoSy?
Neither is better in general; they answer the same question by different means. HSG uses X-ray and gives a permanent image. HyCoSy and HyFoSy use ultrasound with no radiation. The choice depends on your history, whether iodine contrast is suitable, and what else needs to be looked at.
Do I need both tubes open to conceive naturally?
No. One open tube is compatible with natural conception. Both tubes being blocked is what makes natural conception and IUI unviable, and it is the situation IVF is designed for.
When in my cycle should the test be done?
In the first half — roughly days 6 to 12, after bleeding has stopped and before ovulation. Bleeding obscures the images, and testing before ovulation removes any possibility of an early pregnancy being present.
Can I have tubal assessment if I have endometriosis?
Yes, and endometriosis is a reason to assess the tubes rather than a reason to avoid it. It may change which test is chosen — laparoscopy is often preferred, because it can see and treat the endometriosis in the same procedure.
What happens if a blockage is found?
It depends on which tubes, and whether there is fluid. One blocked tube usually changes nothing about the plan. Both blocked points to IVF. A tube swollen with fluid is a hydrosalpinx and is normally dealt with before an embryo transfer. The finding is discussed with you before anything is decided.
General information on fertility investigation is available from the NHS guide to infertility.

Written and medically reviewed by Dr. Vani Sundarapandian, MD, DGO, FRCOG (UK) — founder and Medical Director, Jananam Fertility Centre, Chennai.
This page is general information, not personal medical advice. Which test is right for you is a decision for the clinician who knows your history.


